“Learn about the National Vector-Borne Diseases Control Program, focusing on essential strategies like disease management, integrated vector management, and community health education to combat malaria, dengue, and other vector-borne diseases.”
Table of Contents
National Vector-Borne Disease Control Program (NVBDCP)
“National Vector-Borne Diseases are a significant health concern in India, with the National Vector-Borne Disease Control Program (NVBDCP) at the forefront of prevention and control efforts.”
- Purpose: Central program for controlling diseases spread by vectors like mosquitoes and sand flies in India.
- Diseases Covered: Malaria, Dengue, Lymphatic Filariasis, Kala-azar, Japanese Encephalitis (JE), Chikungunya.
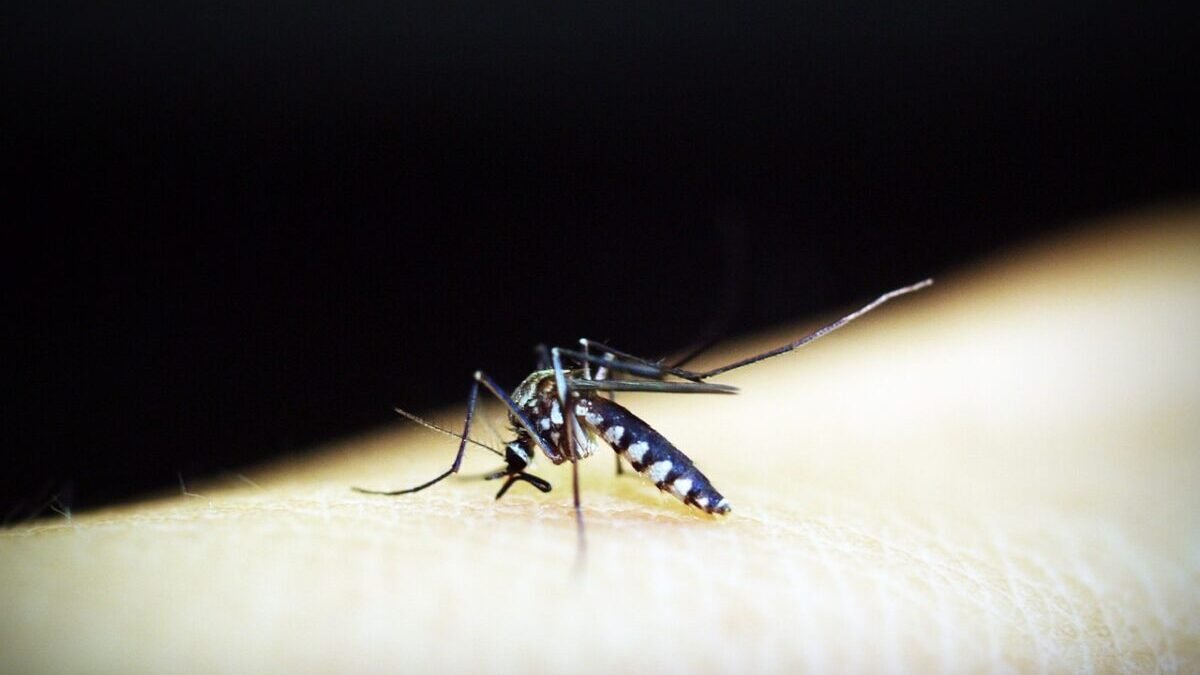
- Transmission: All these diseases are transmitted by mosquitoes except Kala-azar (by sand flies).
Key Strategies
- Disease Management:
- Early detection and complete treatment.
- Preparedness for epidemics and rapid response.
- Integrated Vector Management:
- Indoor residual spray.
- Use of insecticide-treated bed nets.
- Anti-larval measures like source reduction.
- Supportive Interventions:
- Health education and behavior change communication.
- Capacity building and training.
- Intersectoral convergence (collaboration across sectors).
Malaria Control Program
- Vision: Reduce malaria burden and aim for elimination.
- Goal: Achieve an Annual Parasite Index (API) of <1 per 1000 population by 2017.
- Strategies:
- Screening all fever cases for malaria.
- Treating all positive cases promptly and effectively.
Preventive Measures
- Against Larvae:
- Use larvicides in stagnant water (e.g., Temphos, Paris green).
- Against Adult Mosquitoes:
- Spray residual insecticides like DDT.
- Use mosquito nets and repellents.
- Community Protection:
- Promote protective clothing and use of mosquito mesh.
- Educate the community about prevention and management.
Health Education
- Essential for informing the community about the causes, spread, and prevention of vector-borne diseases.
- Use various educational approaches for effective communication.
This summary provides a clear overview of the key points related to National Vector-Borne Diseases and their control.
National Malaria Control Program Under NVBDCP.
- Main Goal: Control and prevent malaria through effective strategies and treatment.
- Diagnosis & Treatment:
- Check for malaria with blood smears (thin and thick).
- Start treatment while waiting for lab results (presumptive treatment).
- Follow the treatment plan based on the type of malaria detected.
- Ensure the first dose is given under observation.
- Role of Community Health Nurse:
- Monitor vital signs of all patients.
- Never ignore any case of fever.
- Educate patients and their families about malaria.
- Advise patients to drink plenty of water and monitor for vomiting after taking medicine.
- If the patient shows signs of severe illness (e.g., drowsiness), refer them to the hospital immediately.
- Follow-up: Regularly check on the patient and their family to ensure recovery and prevent further spread of malaria.
Lymphatic Filariasis Elimination Program: Simple Notes
- Disease Overview:
- Lymphatic filariasis, also known as elephantiasis, is a tropical disease affecting over 120 million people worldwide.
- It causes severe disfigurement and disability in about 40 million people.
- Program History:
- The National Filarial Control Program (NFCP) began in 1955.
- In 2003, it was included in the National Vector Borne Disease Control Program (NVBDCP).
- Training and research are conducted by the National Institute of Communicable Diseases, Delhi.
- Elimination Definition:
- The disease is considered eliminated when less than 1% of the population carries the microfilaria, and new-borns are free from the infection.
- Major Activities:
- Goal: The goal is to eliminate lymphatic filariasis by 2015, as per the National Health Policy 2002.
- Strategies:
- Annual mass drug administration (MDA) with a single dose of antifilarial drugs like DEC and Albendazole for at least 5 years.
- Home-based care for lymphedema and hydrocele surgeries.
- Anti-larval and anti-mosquito measures in endemic areas.
- Improved sanitation, including drainage facilities and preventing water stagnation.
- Health education on environmental cleanliness and use of insect repellents.
- Exclusions from MDA:
- Pregnant women, children under 2 years, and seriously ill people are excluded from MDA.
- Ongoing Efforts:
- Microfilarial surveys and drug administration are regularly conducted to monitor progress.
- Public awareness campaigns encourage regular treatment and home care management.
Kala-Azar Control Program:
- Program Overview:
- The Kala-azar control program is a centrally sponsored initiative launched in 1990-91.
- Before the use of DDT, Kala-azar was highly endemic in India, causing significant economic harm due to high morbidity and mortality.
- Elimination Strategies:
- Enhanced Case Detection: Improved methods for finding and treating cases.
- Rapid Diagnostic Kits: Introduction of PK39 kits for quick diagnosis.
- Oral Drug “Miltefosine”: Used for treating Kala-azar.
- Vector Control: Fogging with pyrethroid instead of DDT to eliminate sandflies.
- Behavioral Impact Communication: Educating the community to encourage cooperation in eradication efforts.
- Capacity Building: Strengthening the skills of healthcare providers.
- Supervision & Monitoring: Regular checks and evaluations to ensure program effectiveness.
- Case Search for Kala-azar:
- Quarterly Searches: More frequent searches, called “Kala-azar fortnight surveys,” involving door-to-door visits.
- Incentives: ASHA workers receive ₹300 per identified case and ₹100 for community support during insecticide sprays. Patients receive ₹500 during hospitalization.
- Revised Eradication Strategy (2014):
- New Diagnostic Tools: Introduction of RDT developed by ICMR.
- New Treatment: Liposomal Amphotericin B (IV 10 mg-single dose) provided free by WHO.
Japanese Encephalitis (JE) Control Program:
- Disease Overview:
- JE is a severe disease causing up to 20,400 deaths annually worldwide.
- Survivors often suffer from long-term neurological issues such as paralysis or seizures.
- The disease is prevalent in rural and peri-urban areas of several Indian states.
- Vector Control Strategies:
- Alternate Wet and Dry Irrigation (AWDI): Helps control mosquito breeding by disrupting their lifecycle in paddy fields.
- Biological Control: Use of natural predators like Gambusia fish to control mosquito populations.
- Chemical Control: Application of deltamethrin, organophosphates, and carbamates to reduce mosquito numbers.
- Health Education:
- Community Involvement: Educate and engage communities in cleaning surroundings and eliminating mosquito breeding sites.
- Personal Protective Measures: Wearing full-sleeved clothing, using mosquito nets, and applying repellents.
- Management:
- No specific treatment is available; supportive care includes feeding, airway management, and seizure control.
- Long-term care and rehabilitation may be needed for survivors.
- Surveillance:
- Clinical Surveillance: Early diagnosis and management of JE patients at primary health centers.
- Vector Surveillance: Monitoring mosquito behavior in risk areas to adapt control measures accordingly.
Dengue Control:
Overview:
- Dengue is prevalent in tropical and subtropical regions worldwide.
- Severe dengue is a leading cause of death among children in some Asian and Latin American countries.
- A significant dengue outbreak occurred in Delhi in 1996.
Government Actions:
- 311 hospitals were identified for laboratory support in endemic areas.
- 14 Apex Referral Laboratories were linked with these hospitals for better case management.
Eight Key Elements for Dengue Prevention and Control:
- Surveillance:
- Continuous monitoring in areas with Aedes aegypti and A. albopictus mosquitoes.
- Sentinel clinics report fever cases (above 38°C) to public health authorities for further blood tests and identification.
- Case Management:
- Focus on laboratory diagnosis and effective clinical management of dengue cases.
- Vector Management:
- Source Reduction: Eliminate breeding sites for mosquitoes.
- Chemical Control: Use of insecticides to control mosquito populations.
- Personal Protection: Encourage the use of mosquito repellents and nets.
- Legal Measures: Implement laws to enforce mosquito control efforts.
- Outbreak Response:
- Epidemic Preparedness: Prepare for potential outbreaks with resources and planning.
- Media Management: Use media to inform the public during outbreaks.
- Capacity Building:
- Training: Provide training for healthcare workers.
- Infrastructure Development: Improve facilities and resources.
- Operational Research: Conduct research to improve dengue control methods.
- Behavioral Change Communication:
- Social Mobilization: Engage the community in dengue prevention efforts.
- Information, Education, and Communication (IEC): Spread awareness about dengue prevention.
- Inter-sectoral Coordination:
- Work together with both health and non-health sectors to control dengue.
- Monitoring and Supervision:
- Regular review, field visits, analysis of reports, and providing feedback for continuous improvement.
Chikungunya and Guinea Worm Disease Control:
Chikungunya Overview:
- The name “Chikungunya” comes from the Kimakonde language, meaning “to become contorted,” referring to the joint pain and stooped posture it causes.
- Chikungunya has spread to over 60 countries, especially in Asia.
- Prevention, control, and surveillance strategies are similar to those used for Dengue.
Role of Community Health Nurse in Chikungunya Control:
- Environmental Control:
- Educate the community on reducing mosquito-breeding sites by eliminating water-filled containers, both natural and artificial.
- Personal Protective Measures:
- Wear clothing that minimizes skin exposure to mosquito bites.
- Treat clothes with permethrin to repel mosquitoes if possible.
- Apply mosquito repellents containing DEET to exposed skin.
- Use insecticide-treated mosquito nets and mosquito coils to prevent indoor bites.
- Install insect screens on windows and doors to keep mosquitoes out.
Guinea Worm Disease (Eradication Program) Overview:
- Guinea worm disease is a disabling parasitic disease that was common in rural areas with step-wells.
- The last case in India was reported in 1996.
- The World Health Organization (WHO) declared India and other South East Asian countries free of Guinea worm disease.
Key Activities in Guinea Worm Eradication:
- Health Education:
- Focus on educating rural women and children about preventing Guinea worm disease.
- Rumor Registration and Investigation:
- Keep track of any rumors about Guinea worm cases and investigate them thoroughly.
- Surveillance:
- Continue monitoring areas previously infected with Guinea worm.
- Maintain Guinea worm disease on the notified list of diseases.
- Safe Water Supply:
- Ensure the proper functioning of hand pumps and other safe drinking water sources to prevent the spread of the disease.
- National Newborn Week 2026: Essential Newborn Care Every Nurse Should Know

- Diabetic Foot Care Nursing: Assessment, Risk Levels and Patient Teaching

- World Diabetes Day 2026: Early Action on Diabetes and the Nurse’s Role

- World Pneumonia Day 2026: Nursing Care, Danger Signs and Prevention

- NORCET Fundamentals of Nursing: High-Yield Points and Practice MCQs
Educational Disclaimer
The information in this article is provided for educational and informational purposes only, aimed at students and faculty in Nursing, Medical, Paramedical, and allied Health Science programmes. It is not medical advice, diagnosis, or treatment, and must not replace guidance from a qualified physician, nurse, or licensed healthcare professional.
While we review all content carefully and align it with recognised syllabi (INC, RGUHS, state nursing councils), medical knowledge evolves rapidly. Always verify clinical procedures, drug doses, and protocols against your institution's current guidelines before applying them in patient care.
For complete terms, see our Disclaimer. Found an error? Let us know.
You May Also Read

Diabetic Foot Care Nursing: Assessment, Risk Levels and Patient Teaching
A practical diabetic foot care nursing guide: IWGDF risk categories, how to assess the foot, the monofilament test, daily self-care teaching and when to refer.

World Diabetes Day 2026: Early Action on Diabetes and the Nurse’s Role
World Diabetes Day 2026 (14 Nov) focuses on early action. Learn India's diabetes figures, NP-NCD screening, warning signs, diagnostic values, hypoglycaemia care and how nurses can lead early action.

World Pneumonia Day 2026: Nursing Care, Danger Signs and Prevention
World Pneumonia Day is on 12 November. Learn the danger signs in children, India's SAANS campaign, PCV schedule, oxygen rules and the nurse's role in care and prevention.

Honey for Wound Healing: Tibb-e-Nabawi Wisdom and Modern Nursing Evidence
What the Qur'an and Sunnah say about honey, what the Cochrane review found about honey for wound healing, and the safety rules every nurse must follow.