Master the top nursing documentation methods and reporting guidelines! Learn the do’s and don’ts, types of reports, and best practices for accurate patient care records.
✅ Discover the types of client records and reports in health care documentation. Learn their purposes, confidentiality rules, and best practices.
Table of Contents
What is Documentation?
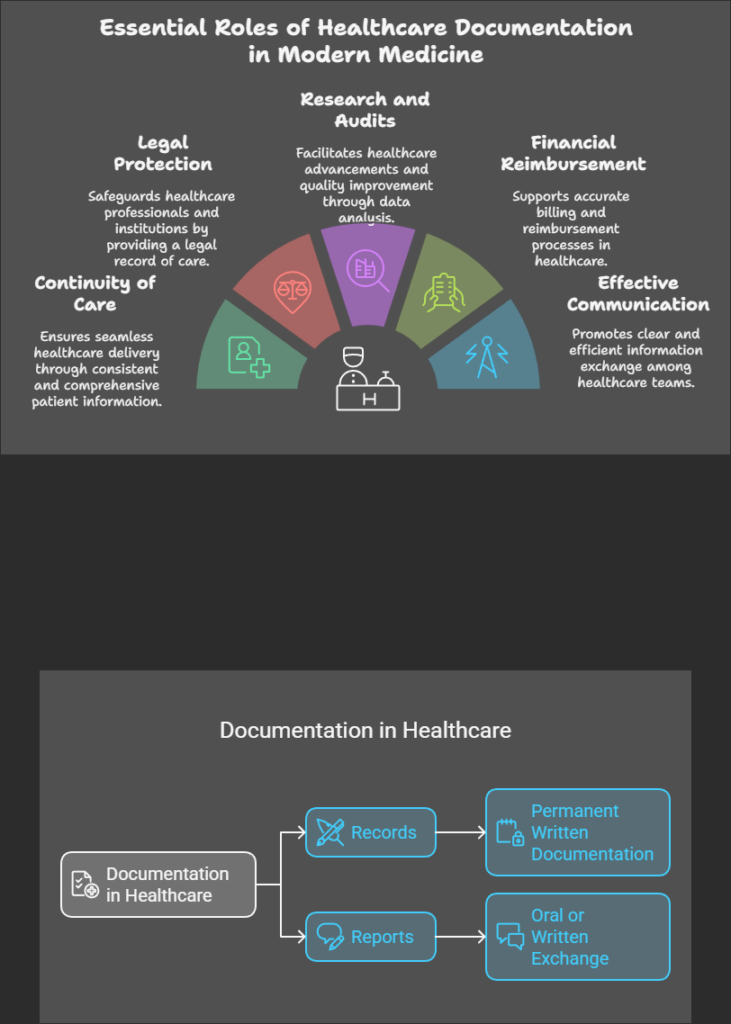
Documentation in healthcare is the process of recording patient information, treatments, and outcomes. It ensures continuity of care, enhances communication among healthcare professionals, and serves as legal and research evidence.
Importance of Documentation in Nursing
Ensures continuity of care
Provides legal protection
Supports research and audits
Aids in financial reimbursement
Enhances effective communication
Documentation in health care
Types of Documentation
Records – Permanent written documentation of patient care.
Reports – Oral or written exchange of information.
Records in Healthcare
A record is a permanent document related to a patient’s healthcare, covering admission to discharge. It serves as a clinical, scientific, administrative, and legal document.
Purpose of Records
Acts as a communication tool among healthcare teams.
Provides data for research and program evaluation.
Helps in legal protection and nursing audits.
Supports continuity of care and planning.
Aids in financial reimbursement and hospital management.
Reports in Healthcare
A report is an oral or written communication used to exchange patient information.
Purpose of Reports
Ensures proper healthcare planning.
Helps in goal setting and service evaluation.
Provides accurate information for legal and administrative purposes.
Assists in public health studies.
Enhances team coordination and efficiency.
Key Purposes of Documentation
Communication – Ensures smooth information transfer among healthcare teams.
Planning Patient Care – Supports personalized treatment plans.
Legal Record – Serves as a legally admissible document.
Education – Acts as a reference for medical students.
Research – Provides data for healthcare improvements.
Audit – Helps in evaluating nursing and hospital services.
Financial Reimbursement – Essential for insurance claims and government funding.
CONFIDENTIALITY
Confidentiality is the protection of personal information. It means keeping client information private and not sharing it with others, including coworkers, friends, or family. Information acquired while at work should not be disclosed to outsiders without written consent from the patient. Only authorized healthcare personnel involved in diagnosis, treatment, and care are entitled to access patient documents.
Managing Data Confidentiality
Consider the following when handling confidential information:
To whom data can be disclosed
Whether laws, regulations, or contracts require data to remain confidential
Whether data may only be used or released under specific conditions
Whether data is sensitive by nature and could have a negative impact if disclosed
Whether data would be valuable to unauthorized parties (e.g., hackers)
The information contained in patient documents is strictly confidential. Patient documents refer to records needed to arrange and provide care. Confidential information includes:
Name, date of birth, age, sex, and address
Current contact details of family or guardians
Medical history and records
Personal care details
Service records and progress notes
Individual care plans
Assessments or reports
Incoming or outgoing personal correspondence
TYPES OF CLIENT RECORDS
Client records are essential to healthcare. All health professionals have a legal and ethical responsibility to maintain accurate client records while ensuring privacy. Good record-keeping is a key component of quality healthcare.
The primary use of client records is to help healthcare professionals understand medical history and identify problems. The client health record is a legal document that helps manage patient care.
Types of Records
1. Outpatient Records
Outpatient records are maintained in the form of outpatient cards. These include:
Referral number
Patient’s biodata
Medical history (past and present)
Family history
Investigation reports
Diagnosis and treatment
Frequency of visits and prognosis
Stored in the outpatient record department
2. Inpatient Records
Inpatient records are a continuation of outpatient records. They document the patient’s stay in the hospital and include:
Admission Records
Medical History Records
Observation Records
Laboratory Investigation Records
Intake and Output Records
Doctor’s Order Sheet
Treatment Records
Diet Records
Prognosis Records
Nurses’ Notes
Discharge Records
3. Nurses’ Records
Nurses maintain essential patient-related records, which are stored in the nurses’ duty room. These include:
Nurse’s Notes
Admission-Discharge Register
Birth Register
Death Register
Accident Record
Duty Roster
Indent Register
Inventory Register
Stock Register
Change of Shift Record
Nurse’s Progress Record
Staff-Patient Assignment Record
COMMON RECORD-KEEPING FORMS
A variety of forms are used to document a client’s health status, problems, and responses to interventions. These include:
1. Nursing Kardex
The Nursing Kardex is a client profile and summary sheet. It consists of index cards stored in a specific location or portable file. It contains essential patient information and serves as a quick reference for nurses throughout their shifts and during handovers.
The Kardex should be updated with every change in patient orders and used as a communication tool between shifts. It typically includes:
Basic demographic data
Primary medical diagnosis
Nursing care plan
Laboratory tests
Physician’s orders
2. Nursing History Form
The Nursing History or Nursing Assessment Form is completed upon a client’s hospital admission. It includes a comprehensive assessment to identify relevant nursing diagnoses. This form provides baseline data for monitoring changes in the client’s condition. It generally records:
Allergies
Advance directives
Disabilities and mobility status
Medication reconciliation
Each hospital may have its own standardized nursing history form based on practice guidelines.
3. Graphic and Flow Sheets
Flow sheets contain vertical and horizontal columns for recording data over time, helping to track client conditions and interventions efficiently. They are particularly useful for documenting:
Vital signs
Intake and output
Hygiene measures
Medication administration
Pain assessment
IV therapy
Flow sheets provide a quick reference in clinical settings, especially in critical care units. However, significant changes or unusual events should still be documented in progress notes.
4. Nurse’s Progress Notes
Nurses’ progress notes document client problems, complaints, interventions, responses, and progress toward goals. They may follow various documentation formats, such as SOAP (Subjective, Objective, Assessment, Plan), PIE (Problem, Intervention, Evaluation), or focus charting.
Progress notes may include:
Nurse’s notes
Medication Administration Record (MAR)
Personal care flow sheets
Teaching records
Intake and output forms
Vital signs records
Diabetic assessment forms
Neurological assessment forms
5. Standardized Care Plans
Standardized care plans are based on institutional nursing practice standards. The nurse first conducts an assessment. Then, the nurse prepares a care plan tailored to the client’s needs. Finally, the plan is placed in the medical record.
Standardized care plans improve continuity of care. However, they have some limitations. These limitations include inhibiting individualized therapy and potentially replacing nurses’ critical thinking. They must be updated regularly.
A standardized care plan typically consists of five columns:
Nursing Diagnosis – Prioritized based on severity
Expected Outcomes – Goals for the patient’s recovery
Nursing Care Interventions – Actions taken to address the diagnosis
Scientific Rationale – Justification for interventions
Evaluation – Assessment of intervention effectiveness
S. No
Nursing Diagnosis
Expected Outcome
Nursing Care
Scientific Rationale
Evaluation
standardized nursing care plan format
6. Discharge Summary Forms
A discharge summary ensures a well-coordinated transition from hospital to home. It emphasizes early recovery, reduced hospitalization time, and continued care.
The discharge summary includes:
The client’s condition at admission and discharge
A summary of care received
Interventions and education outcomes
Resolved and unresolved problems requiring follow-up
Client instructions on medications, diet, safety, follow-ups, and other special needs
Family roles and responsibilities in continuing care
A copy of the discharge summary is given to the client, while another is kept in the medical record.
Counselling plays a crucial role in empowering individuals to make informed decisions and achieve mental well-being. This post explores counselling types, the counselling process, essential tools and techniques, and the role of health education in enhancing its impact.
“Explore essential principles of health education, key approaches to public health education, and the stages of behavior change to transform health outcomes.”
“Discover the key principles of communication, its process, types, barriers, and the art of observing and listening skills. Learn how effective communication can transform your interactions.”
Table of Contents
Introduction
Communication originates from the Latin word “communicare,” meaning to participate, inform, or impart.
It involves the exchange of thoughts, experiences, views, opinions, information, and facts among individuals or groups.
Effective communication in health education can motivate individuals and groups toward health protection.
Definition of Communication
General Definition: The process of exchanging information, thoughts, ideas, and feelings between individuals.
Detailed Definition:
Includes all actions taken to create understanding in another person’s mind.
Ensures information, purpose, and attitudes are shared to achieve a common goal.
Aims for the message to be received and understood as intended.
Process of Communication
The communication process consists of seven stages, involving a sender, message, channel, receiver, and feedback.
Source/Sender: The individual or medium delivering the information.
Ideas: The message’s content or subject matter.
Encoding: Converting ideas into codes like words, actions, or images.
Channel: The medium through which the message is sent (e.g., radio, phone, speech, TV).
Receiver: The person for whom the message is intended.
Decoding: Interpreting the codes to understand the message.
Feedback: The receiver’s response, confirming if the message was understood as intended.
Morale Boosting: Enhance group morale among workers.
Job Satisfaction: Ensure contentment in the workplace.
Problem-Solving: Aid in grievance handling and disciplinary actions.
Community Engagement: Inform the public about available services.
Change Management: Prepare personnel and the public for transitions.
Principles of Communication
Effective communication follows these core principles:
Clarity
Focuses on specific goals or messages.
Promotes easier understanding through exact and appropriate words.
Completeness
Ensures all necessary information is conveyed.
Addresses audience needs with relevant facts and figures.
Conciseness
Communicates with minimal words while retaining the essence.
Saves time and emphasizes the core message.
Consideration
Adapts to the audience’s mindset, emotions, and educational level.
Respects the audience’s self-esteem and avoids harm to feelings.
Correctness
Avoids grammatical errors and ensures precision in facts.
Uses appropriate language to boost confidence and impact.
Concreteness
Relies on specific facts to avoid ambiguity.
Builds reputation and strengthens confidence through clear messaging.
Courtesy
Reflects politeness and respect for the receiver.
Maintains a positive tone and avoids bias.
Types of Communication
One-Way Communication
Information flows only from the sender to the receiver (e.g., lecture method).
Drawbacks:
Imposes knowledge and lacks audience participation.
No feedback, limiting behavior influence.
Two-Way Communication
Interactive communication involving both sender and receiver (e.g., Socratic method).
Advantages:
Encourages active participation and democratic learning.
More effective in influencing behavior.
Verbal Communication
Involves spoken or written words.
Features:
Spoken words can be persuasive with hidden meanings.
Written communication is less persuasive but precise.
Non-Verbal Communication
Uses gestures, facial expressions, posture, and silence.
Examples: Smiles, frowns, raised eyebrows, and body language.
Can often convey more than words.
Formal and Informal Communication
Formal: Follows structured lines of authority.
Informal: Exists as social networks like gossip circles.
Visual Communication
Includes charts, graphs, pictograms, maps, posters, and tables.
Telecommunication
Uses mass communication media (e.g., radio, TV, internet) and point-to-point systems (e.g., telephone, telegraph).
Importance of Communication
Nursing: Facilitates understanding between nurses, patients, relatives, and the healthcare team.
Interpersonal Relations: Reduces tensions and improves relationships.
Patient Care: Poor communication can lead to inadequate care.
Behavioral Influence: Enables nurses to modify their behavior and influence others effectively.
Organizational Efficiency: Prevents disorder and facilitates policy interpretation in hospitals.
Barriers to Communication
Physiological
Hearing difficulties or inability to express thoughts.
Psychological
Emotional disturbances, neurosis, language comprehension issues, or varying intelligence levels.
Environmental
External factors like noise, congestion, and invisibility hinder effective communication.
Cultural
Differences in literacy, customs, beliefs, religion, language, and socioeconomic status.
Social and cultural barriers can obstruct health behavior changes, even when services are accessible.
Solution: Identify and address these barriers for effective communication.
Establishment of Successful Communication: Key Aspects
Successful health communication is essential for improving public health, promoting positive behaviors, and enhancing the effectiveness of healthcare services. Below are the key elements and principles for establishing effective communication:
Primary Needs Addressed by Health Communication
Information
Provides factual, scientific knowledge to the public about health issues and methods to maintain and promote health.
Key Factors:
Eliminating ignorance, prejudice, and misconceptions.
Collaboration of the government, media, and health providers to disseminate accurate information.
Education
Education is rooted in communication, forming the foundation for health literacy and awareness.
Motivation
Encourages individuals to progress through:
Awareness → Interest → Decision-Making → Adoption of Behaviors.
Persuasion
Influences beliefs, values, and behaviors through targeted messaging.
Benefits:
Lifestyle changes.
Reduction of risk factors for diseases.
Counseling
Assists individuals in understanding and managing their problems.
Relies heavily on relationship-building and communication skills.
Raising Morals
Enhances team spirit and cohesion among healthcare teams.
Communication fosters collective determination and resilience.
Health Development
Spreads knowledge about health goals, facilitating progress in public health initiatives.
Health Organization
Communication serves as the backbone of organizational operations.
Types of Communication:
Vertical Communication:
Downward: From administrators to staff and beneficiaries.
Upward: From staff to higher management.
Horizontal Communication: Between peers at the same organizational level.
Facilitates intersectoral coordination within healthcare organizations.
Observing and Listening Skills in Communication
Effective communication relies heavily on listening and observation skills. These abilities enhance understanding, foster empathy, and facilitate meaningful interactions, especially in health education. Below is a detailed exploration of these skills:
Art of Listening in Communication
Listening is a critical yet often overlooked component of communication. While speaking might seem more impactful, being an attentive listener is a hallmark of effective communicators, particularly in health education.
Characteristics of a Good Listener
Active Listening: Listening attentively, with focus and patience, rather than passively remaining silent.
Understanding: Fully comprehending the speaker’s concerns, emotions, and messages.
Evaluating: Assessing the information for accuracy and relevance to health education.
The LADDER Approach to Effective Listening
L: Look at others and maintain good eye contact.
A: Ask appropriate and relevant questions.
D: Do not interrupt the speaker.
D: Do not change the subject.
E: Express emotions with control.
R: Responsively listen, providing feedback and encouragement.
Benefits of Good Listening Skills
Enhances personal development and relationships.
Saves time by identifying the root of problems.
Clarifies objectives and facilitates effective feedback.
Observation in Communication
Observation involves gathering information about people, events, and situations through careful inspection. In health education, observation is crucial for understanding community dynamics and individual needs.
Definition
“Observation means to see events in the right perspective and record them to understand the relationship between causes and effects.”
Characteristics of Effective Observation
Use of Special Senses: Utilizing sight, hearing, and speech for detailed inspection.
Minuteness: Paying attention to even the smallest details.
Cause-Effect Analysis: Identifying relationships between actions and outcomes.
Impartiality: Remaining unbiased and objective during observation.
Empirical Study: Observations should be based on real-world evidence.
Types of Observation
Participatory Observation: Observer actively participates in activities.
Non-Participatory Observation: Observer remains a passive onlooker.
Semi-Participatory Observation: Combines elements of active and passive participation.
Controlled Observation: Conducted under predefined conditions.
Uncontrolled Observation: Occurs in natural, uncontrolled environments.
Guidelines for Health Education Observation
Clarity: Observations must align with the subject matter.
Focus: Target observations to immediate issues, e.g., checking dietary habits for anemia.
Objective-Oriented: Clear goals for the observation process.
Techniques and Methods: Observers should be trained and experienced.
Communication Expertise: Strong communication skills enhance observational accuracy.
Limitations of Observation
Potential biases or favoritism from the observer.
Limited ability to cover all events or scenarios.
Subjectivity in interpreting reactions and behaviors.
The nursing process is a vital framework that guides nurses in delivering comprehensive patient care. It starts with a detailed nursing assessment, followed by a precise nursing diagnosis. These initial steps ensure that the care plan is accurate, personalized, and effective in improving patient outcomes. This article will provide an in-depth look at the process, ensuring you understand each stage and its importance in nursing practice.
Explore the concept of Primary Health Care with an epidemiological approach and evidence-based practice. Learn how empowering people to care for themselves is key in community health nursing.
Table of Contents
Epidemiological Approach
Key Highlights
Historical Foundation:
Florence Nightingale (1820–1910) was a statistician. She used epidemiological approaches during the Crimean War. She represented preventable deaths among soldiers through statistical methods.
Definition of Epidemiology:
“The study examines the distribution and determinants of health-related states or events in specified populations. It applies this study to the prevention and control of health problems.” (Last, 1988)
Core Components of Epidemiology: a. Distribution
Frequency: Relationship between the number of health events and population size (e.g., cases of diabetes per population size).
Person: Demographics (age, gender, socioeconomic status) and behaviors.
b. Determinants
Factors or root causes influencing health events (e.g., environmental exposures, behaviors).
Analytical epidemiology helps identify these determinants.
c. Health-Related States or Events
Initially focused on communicable diseases, now includes non-communicable diseases and overall well-being.
Focus on Populations:
Specified Populations:
Physicians focus on individuals, while epidemiologists focus on communities or populations.
The epidemiologist’s “patient” is the community.
Applications:
Community-Based Practice:
Diagnosis of community health forms the basis for public health interventions.
Aim: To prevent and control diseases through feasible, relevant, and acceptable measures.
Importance of Epidemiology in Nursing:
Provides tools for scientific inquiry and public health foundations.
Combines biostatistics, informatics, and social sciences to assess health states/events.
Facilitates designing effective health programs and interventions.
Using Epidemiological Approach in Community Health Nursing
Key Highlights
Surveillance of Disease and Health Status:
Importance of Surveillance:
Provides insight into the health status of the community.
Helps identify new, emerging, and re-emerging diseases.
Aids in planning, prioritization, and budgeting for health programs.
Role of Surveillance Data:
Estimates the magnitude of health problems.
Tracks the natural history and unusual presentations of diseases.
Identifies endemic diseases and detects epidemics for timely action.
Sources of Surveillance Data:
Records, registers, government reports, and management information systems (MIS).
Search for Etiology:
Audits and Reviews:
Perinatal, maternal, and under-five mortality audits provide insights into underlying causes.
Data sources include government and private agencies.
Evaluating Care:
Explores the effectiveness of care at facilities like sub-centers and primary health centers (PHCs).
Descriptive Epidemiological Approach in Nursing:
Defining the Population:
Study either the entire population or a representative sample.
Defining the Disease:
Describe the disease in terms of:
Time: When the disease occurs (e.g., year, season, hour).
Place: Where it occurs (e.g., geographic zones, urban/rural areas).
Person: Who is affected (e.g., age, sex, social status).
Analyzing Patterns:
Compare present patterns with past trends or across regions/countries.
Formulating Hypotheses:
Use descriptive data to hypothesize causes, later tested through analytical epidemiology.
Investigating Food Poisoning:
Steps in Investigation:
Identify affected individuals and gather details on food consumption:
What, where, and when they ate.
Symptoms experienced and their onset.
Other affected individuals in the group or region.
Check for events or travel histories that may explain exposure.
Outcome:
Helps pinpoint the source and cause of food poisoning.
Importance of Epidemiological Approach
Provides data-driven insights for community health improvement.
Enhances early detection and prevention of outbreaks.
Supports evidence-based decision-making in public health nursing.
Problem-Solving Approaches in Nursing
Key Highlights
Definition and Importance:
Problem-solving involves applying a structured theoretical model for decision-making.
Decision-making, a critical part of problem-solving, relies on critical-thinking skills.
Traditional Problem-Solving Approach
Widely recognized and involves 7 sequential steps:
Identify the problem.
Gather data to analyze causes and consequences.
Explore alternative solutions.
Evaluate alternatives.
Select the appropriate solution (decision-making).
Implement the solution.
Evaluate the results.
Weakness: Lacks an explicit goal-setting step.
Managerial Decision-Making Process
An enhanced version of the traditional model, addressing its limitations.
Steps include:
Set objectives.
Search for alternatives.
Evaluate alternatives.
Choose a solution.
Implement the solution.
Follow-up and control.
Nursing Process as a Decision-Making Model
A widely used approach in nursing for problem-solving and decision-making.
Similar to the managerial decision-making process but incorporates a feedback mechanism for continuous improvement.
Steps:
Assessment:
Collect data and identify the problem.
Planning:
Identify criteria and explore alternatives.
Implementation:
Implement the selected alternative.
Evaluation:
Evaluate the outcomes and make adjustments.
Key Advantage:
The feedback mechanism ensures ongoing assessment and improvement, setting it apart from traditional and managerial models.
Evidence-Based Practice (EBP) Approach in Community Health Nursing
Definition
Evidence-Based Practice (EBP) is the conscientious, explicit, and judicious use of current best evidence to make informed decisions about patient care.
Integrates clinical expertise, patient values, and research evidence for decision-making (Sackett, 1996).
In community health nursing, clinical expertise equates to the nurse’s experience, education, and skills, while patient values include preferences, concerns, and expectations.
Elements of EBP
Best Research Evidence: From rigorously conducted studies.
Clinical Expertise: The knowledge and skills of community health nurses.
Patient Values: Preferences, expectations, and value systems.
Improved Patient Outcomes: The ultimate goal of EBP.
Steps in Evidence-Based Practice
Develop a Clinical Question:
Construct a well-defined question based on observations or gaps in knowledge.
Assess Existing Evidence:
Determine if sufficient evidence exists or if further exploration is needed.
Apply Methodology (e.g., PICO):
Use structured approaches like PICO to guide research and interventions.
PICO Method
A systematic approach to defining and answering clinical questions:
P: Patient/Population of interest (e.g., infants, pregnant women, high-risk groups).
I: Intervention of interest (e.g., a specific treatment or practice).
C: Comparison of interest (e.g., no treatment, placebo, or standard care).
O: Outcome of interest (e.g., reduced malnutrition rates, improved health).
T: Time frame (e.g., duration of the intervention).
Example Question Using PICO: “Does the incidence of protein-energy malnutrition among infants (P) in village A decrease (O) with the administration of nutritious balls (I) for 6 months compared to infants in village B (C)?”
Other Methods
PICOT: Adds “Time” as a component to PICO.
PESICO: Includes Person, Environment, Stakeholders, Intervention, Comparison, and Outcome (Schlosser & Costello, 2007).
Advantages of EBP in Community Health Nursing
Promotes individualized care by integrating evidence with patient preferences.
Helps community health nurses question outdated practices and adopt scientifically validated approaches.
Drives innovation and improves health outcomes in populations.
Empowering People to Care for Themselves: Community Health Nursing Perspective
Definition and Importance of Community Empowerment
Community Empowerment: A process enabling communities to gain greater control over their lives (Laverack, 2008).
Promotes shared values, concerns, and identities within communities.
Empowers individuals to take ownership of their health, making them assets in their own care.
People’s Ownership of Their Own Health
Encourages self-reliance in health management.
Role of External Agencies: Serve as catalysts to guide and support communities in gaining control over their health.
Community Health Nurses (CHNs):
Use participatory approaches to enhance knowledge and encourage self-responsibility.
Role of Health Literacy in Empowerment
CHNs strive to improve access to health information and help communities use it effectively.
Health Literacy vs. Health Education:
Health literacy addresses behavioral, environmental, political, and social determinants of health, going beyond traditional education.
Resilient Health Systems
Characteristics of a resilient health system:
Universal reach
Adequate workforce
Community participation mechanisms
Strong financial and leadership base
Strengthening health systems is a key strategy for health promotion.
Health Care Concepts in India: A Timeline
1. Comprehensive Health Care (1946)
Introduced by the Bhore Committee, focusing on integrated services.
Features:
Preventive, curative, and promotive services.
Accessibility to all beneficiaries, especially vulnerable groups.
Close provider-beneficiary cooperation.
Focus on healthy environments at home and workplaces.
2. Basic Health Services (1965)
Concept introduced by UNICEF and WHO, emphasizing coordinated efforts between peripheral and intermediate health units.
Key Features:
Assurance of competent professionals and auxiliary staff.
Similar to comprehensive health care but lacked community participation and intersectoral coordination.
Concept of Primary Health Care
The Primary Health Care (PHC) approach was established in 1978 during the Alma-Ata Conference in the USSR. It emphasizes equitable, universal health care accessible to all individuals, irrespective of their socioeconomic status. The conference defined PHC as:
“Essential health care is made universally accessible to individuals. It is acceptable to them through their full participation. This is achieved at a cost that the community and country can afford.”
Core Elements of Primary Health Care
Health Education: Focus on preventing and controlling health issues.
Nutrition Promotion: Ensuring proper food supply and nutrition.
Safe Water and Sanitation: Provision of clean water and basic sanitation.
Maternal and Child Health: Including family planning services.
Immunization: Protection against major communicable diseases.
Control of Endemic Diseases: Measures to prevent and manage local outbreaks.
Treatment of Common Illnesses and Injuries.
Access to Essential Drugs.
Principles of Primary Health Care
1. Equitable Distribution
Health services must be accessible to all, regardless of wealth or location.
Addresses social injustice, ensuring equal distribution of resources, especially to underserved rural and urban slum populations.
2. Community Participation
Encourages involvement of individuals, families, and communities in planning, implementing, and evaluating health services.
Examples:
Village health guides in India.
Barefoot doctors program in China.
3. Multisectoral Coordination
Collaboration among various sectors like agriculture, housing, education, and public health to ensure comprehensive care.
Examples of Coordination:
Maternal care: Involves health departments, family welfare, and community nurses.
Communicable diseases: Requires cooperation among sanitation, agriculture, urban development, and healthcare sectors.
4. Appropriate Technology
Technology should be:
Scientifically sound
Adaptable to local needs
Affordable and maintainable by the community.
Promotes self-reliance and aligns with the philosophy of “health by the people.”
5. Focus on Prevention
Prevention is the cornerstone of PHC, with activities targeted at all levels of disease progression:
Levels of Prevention in Primary Health Care
Primary Prevention
Focus: Health promotion and disease prevention.
Purpose: Reduce exposure to health risks before disease onset.
Examples:
Immunizations against communicable diseases like polio.
Educating young adults on healthy lifestyles.
Promoting safety measures for the elderly.
Secondary Prevention
Focus: Early detection and intervention.
Purpose: Limit the progression of existing health issues.
Examples:
Cervical cancer screening (Pap smears).
Hypertension and cholesterol checks.
Tertiary Prevention
Focus: Rehabilitation and restoring optimal function.
Purpose: Minimize disability and improve quality of life.
Explore the top 5 approaches to community health nursing. These include Nightingale’s Environmental Theory, Neuman’s Systems Model, and Pender’s Health Promotion Model. Learn their scope and relevance today!
Table of Contents
Approaches in Community Health Nursing.
Holistic Nursing Approach
Defined by the American Holistic Nurses Association as “all nursing practice that has healing the whole person as its goal.”
Focuses on the complete person, beyond the physical body.
Rooted in principles established by Florence Nightingale.
Settings of Nursing Practice
Nursing service in hospitals
Nursing service in the community
Key Approaches Used in Community Health Nursing
Nursing Theories and Nursing Process
Epidemiological Approach
Evidence-Based Practice (EBP) Approach
Empowering People to Care for Themselves
Nursing Theories and Nursing Process
Concepts of Nursing Theory
Definition: A systematically interrelated set of concepts or hypotheses to explain or predict phenomena.
Functions:
Describes, explains, predicts, and prescribes phenomena in nursing practice.
Guides nursing processes and provides a foundation for nursing autonomy and professionalism.
Phases of Theory Application
Analyzing concepts
Constructing relationships
Testing relationships
Validating relationships
Distinction Between Theory and Model
Theory: A systematic framework for understanding phenomena.
Model: A hypothetical or theoretical representation of real-world processes (e.g., hospital organizational chart).
Application of Theories in Community Health Nursing
Scope and Influence
Theories provide a foundation for community health nursing practice across various specialties and levels.
Influence on nursing practice (Fawcett, 1992):
Identify standards, settings, processes, and technologies for nursing care.
Direct delivery of nursing services and quality assurance programs.
Guide development of systems like care plans, admission databases, and discharge summaries.
Key Outcomes of Theory Integration
Improved autonomy and professionalism in nursing.
Evidence-based and systematic delivery of nursing care.
Enhanced understanding of complex realities in nursing practice.
Key Concepts in Nursing Theories and Models
Nursing theories and models are built on four central concepts:
Client/Patient (Person): Refers to individuals or groups, focusing on their interaction with health and environment.
Health: Encompasses well-being, optimal functioning, and the effects of nursing interventions.
Environment: Highlights the influence of physical and social surroundings on health.
Nursing: Involves the actions and processes that bring about positive health outcomes.
Person and Health: Focuses on life processes, well-being, and optimal functioning, whether individuals are sick or well.
Person and Environment: Examines human behavior in relation to their environment during normal and critical life events.
Health and Nursing: Emphasizes nursing actions that promote positive health changes.
Person, Environment, and Health: Addresses the interaction between individuals and their environment, aiming for holistic care.
Florence Nightingale’s Theory of Environment
Core Principles
Nursing optimizes conditions for nature to act on the patient.
Focuses on a clean, healthy environment as crucial for healing and health maintenance.
Key Concepts in Nightingale’s Theory
Human Beings:
Emphasizes the relationship between individuals and their environment.
Does not specifically define “person.”
Environment:
Central to health, with importance placed on fresh air, light, warmth, cleanliness, quiet, and proper diet.
Poor environments lead to stagnant air and sickness.
Health:
Views health promotion as integral to nursing, focusing on both the sick and the healthy.
Nursing:
Nurses act as observers, facilitating healing by ensuring a healthy environment.
Nursing is an art, while medicine is a science.
Key Statements from Nightingale (1859/1992)
Health of Houses: Poorly designed houses affect the healthy as badly as poorly constructed hospitals affect the sick.
Ventilation and Warming: Maintain pure air for the patient without causing chilling.
Five Essentials for Healthful Houses: Pure air, pure water, efficient drainage, cleanliness, and light.
Assumptions of Nightingale’s Theory
“Nature alone cures,” and a healthy environment supports healing.
Nurses should meticulously observe and report patient conditions.
Nurses must follow medical plans honestly but with autonomy.
Importance of Nightingale’s Theory in Modern Nursing
Focus on Environment: Forms the basis for community health nursing practices.
Health Promotion: Highlights the role of nurses in preventive and promotive health care.
Holistic Approach: Emphasizes caring for patients in their entirety—body, mind, and environment.
Betty Neuman’s Systems Theory:
Betty Neuman’s Systems Theory emphasizes how a patient/client system responds to environmental stressors. It focuses on using nursing interventions at primary, secondary, and tertiary levels. These interventions promote wellness and stability.
Basic Assumptions of Neuman’s Systems Theory
Patient System:
A unique combination of factors and characteristics that respond dynamically to stressors.
Includes a normal line of defense (baseline health) and a flexible line of defense (temporary protection from stressors).
Stressors:
Known, unknown, or universal elements that disturb stability.
Lines of Defense:
Flexible Line of Defense: Protects the system temporarily; breaks down under severe stress.
Normal Line of Defense: Indicates usual stability; deviations signal health issues.
Lines of Resistance: Internal factors that realign the system to wellness after stress.
Dynamic Interaction:
The patient system constantly interacts with the environment, engaging in energy exchanges.
Levels of Prevention in Nursing Interventions
Primary Prevention:
Focuses on risk reduction and preventing stressors before they impact the system.
Example: Health education to prevent illness.
Secondary Prevention:
Reduces the harmful effects of stressors through early treatment.
Example: Screening for diseases.
Tertiary Prevention:
Aims to restore wellness and reconstitute the system.
Example: Rehabilitation after illness.
Application of Neuman’s Theory at Community Level
Represented through concentric circles:
Core: Basic amenities for survival and resource utilization (e.g., food, water, shelter).
Lines of Resistance: Community efforts like population control and health education.
Normal Line of Defense: Existing systems like healthcare infrastructure and sanitation regulations.
Flexible Line of Defense: Dynamic buffers such as disaster preparedness and road maintenance.
Example: Disaster alert systems functioning as a flexible line of defense to protect the community.
Application at Individual Level
Person:
An open system comprising five interrelated variables:
Physiological (biological functions)
Psychological (mental health)
Sociocultural (social and cultural influences)
Developmental (growth and life stages)
Spiritual (belief systems and values)
Health:
A dynamic state of stability when all systems function harmoniously.
Wellness exists when the normal line of defense remains intact.
Environment:
Includes internal, external, and created stressors that influence health positively or negatively.
Nursing:
A holistic approach to promote wellness at individual, family, and community levels.
Uses primary, secondary, and tertiary prevention modes to achieve optimal wellness.
Nursing Response to Stressors
Flexible Line of Defense Activation:
Alarms the system to protect the normal line of defense.
Failure leads to deviation from normal health and illness development.
Continuous Stress Exposure:
Weakens defenses, causing instability and illness.
Key Features in Application
Focuses on holistic care, addressing physical, mental, social, and spiritual dimensions.
Utilizes prevention-based interventions to maintain and restore stability.
Adaptable to both individual and community-level care, ensuring broad applicability in nursing practice.
Roy’s Adaptation Model:
Developed by Sister Callista Roy, this model is a framework grounded in systems theory. Its primary goal is to assist clients in achieving their highest level of functioning through adaptation. The model views individuals as biopsychosocial beings continuously interacting with their environment and adapting to stimuli.
Core Concepts
1. Person (Man)
A dynamic entity with input (stimuli) and output (behavior).
Individuals are influenced by internal and external stimuli and adapt through a continual process.
Outputs (behaviors) result from attempts to adapt to inputs and can be adaptive or maladaptive.
2. Adaptation Modes
Roy identified four key modes through which individuals adapt:
Physiological Mode: Adaptation via internal physiological processes (e.g., maintaining homeostasis).
Self-Concept Mode: Adaptation shaped by life experiences and personal perceptions.
Role-Function Mode: Adaptation related to one’s roles in society and expectations of those roles.
Interdependence Mode: Adaptation through relationships and interactions with others.
3. Health
Health exists on a continuum from perfect wellness to complete illness.
Defined by the ability to adapt to internal or external stimuli.
Example: A nursing student facing psychological trauma but successfully adapting demonstrates a high degree of health.
4. Environment
The environment encompasses all internal and external factors influencing behavior.
Categorized stimuli:
Focal Stimulus: The immediate stimulus requiring adaptation.
Contextual Stimuli: Other contributing stimuli present in the situation.
Residual Stimuli: Environmental factors with unknown effects on the individual.
5. Adaptation
A process and outcome involving conscious awareness, choice, and integration of human and environmental factors.
Coping mechanisms may be innate (natural) or acquired (learned).
Application in Nursing
1. Nursing Process
The nurse’s role is to assist the patient in overcoming stimuli through the four adaptive modes. This process involves:
Behavioral Assessment (Output):
Identify adaptive or maladaptive responses.
Example: A suspected tuberculosis patient’s physical symptoms (e.g., fever, cough, weight loss) are evaluated first.
Stimuli Assessment (Input):
Assess focal, contextual, and residual stimuli.
Example: Investigate sputum for TB bacteria, household crowding, dietary habits, or socioeconomic factors.
Nursing Diagnosis:
Identify whether the patient’s behavior is adaptive or maladaptive.
Goal Setting and Planning:
Manipulate stimuli to promote optimal adaptation.
Implementation and Evaluation:
Intervene and assess outcomes to determine if goals are met.
2. Example Application
For a community health nurse managing a tuberculosis case:
Behavioral symptoms (fever, cough, fatigue) are documented.
Environmental stimuli (crowded living conditions, dietary patterns) are assessed.
A plan is implemented to address stimuli and promote adaptation (e.g., health education, treatment adherence).
Key Definitions in Roy’s Adaptation Model
Adaptation: Conscious processes for achieving harmony between individuals and their environment.
Stimulus: The interaction point between a human system and the environment that provokes a response.
Focal Stimulus: The immediate concern (e.g., illness).
Contextual Stimuli: Related influences (e.g., family dynamics, work stress).
Residual Stimuli: Factors with unknown or unclear effects.
Self-Concept: Beliefs and feelings about oneself at a given time.
Role: Functional societal units tied to others for relational integrity.
Interdependence: Relationships that meet needs for affection, development, and resource sharing.
Orem’s Self-Care Model, developed by Dorothea E. Orem, emphasizes the critical role of self-care in maintaining health and managing illness. The model integrates three interrelated theories, offering a comprehensive framework for nursing practice. Below is an organized summary of its key components:
Concepts of Orem’s Self-Care Model
1. Core Theories
Theory of Self-Care:
Focuses on the activities individuals initiate to maintain life, health, and well-being.
Self-care includes universal requisites like air, water, food, rest, and social interaction, among others.
Theory of Self-Care Deficit:
Occurs when individuals cannot meet their self-care demands.
Nursing intervention is required to bridge the gap between self-care demands and the patient’s abilities.
Theory of Nursing Systems:
Describes the nursing care required based on the patient’s ability to perform self-care.
Three nursing care systems:
Wholly Compensatory: For individuals unable to perform self-care.
Partially Compensatory: For individuals needing assistance with some self-care activities.
Supportive-Educative: For individuals capable of self-care but requiring guidance or education.
Key Components of the Model
Person:
A biopsychosocial being capable of self-care.
The core of the model revolves around the individual’s ability to perform self-care to maintain life and optimal health.
Health:
Defined as the individual’s capacity to adapt to the environment and maintain functioning through self-care.
Self-Care Deficit indicates a state of illness where individuals cannot meet one or more self-care requisites, such as:
Air, water, and food.
Waste excretion.
Activity and rest.
Social interaction and solitude.
Safety from hazards.
Mental well-being.
Environment:
Seen as a negative influence on self-care abilities.
Includes physical and social factors that affect health and distract from self-care activities.
Nursing:
The nurse’s primary role is to fill self-care deficits by providing care or empowering the patient to regain self-care abilities.
Nursing care focuses on:
Enhancing the patient’s independence.
Promoting health education and development.
Nursing Process and Application
Assessment:
Identify self-care deficits by evaluating the patient’s needs and abilities.
Planning:
Categorize the patient into one of the nursing systems (wholly compensatory, partially compensatory, or supportive-educative).
Develop a care plan tailored to their needs.
Implementation:
Use one or a combination of the following five nursing methods:
Acting for the patient.
Guiding the patient.
Supporting the patient (physically or psychologically).
Providing an environment conducive to development.
Teaching the patient self-care.
Evaluation:
Assess the outcomes of nursing interventions and adjust the care plan if necessary.
Applications in Community Nursing
Promoting healthy lifestyles and self-care practices.
Providing partial or full compensatory care in:
Extended care facilities.
Terminally ill centers.
Old age homes.
Supporting families to meet self-care needs during chronic illnesses or rehabilitation.
Nola J. Pender’s Health Promotion Model (HPM)
The Health Promotion Model (HPM) by Nola J. Pender, first introduced in 1982 and revised in 1996, emphasizes a proactive approach to health. Unlike models focusing on disease prevention, HPM seeks to improve overall well-being and promote healthy behaviors. Below is a structured summary of the model’s components:
Key Concepts of HPM
Health
Defined as a positive dynamic state, not merely the absence of disease.
Health promotion aims to enhance well-being and enable individuals to reach higher levels of health.
Person
Viewed as a multidimensional being who interacts with the environment to pursue health.
Focus Areas of the Model
HPM centers around three major components:
Individual Characteristics and Experiences
Behavior-Specific Cognitions and Affect
Behavioral Outcomes
1. Individual Characteristics and Experiences
Personal Factors
Personal factors are predictors of behavior and vary based on the nature of the health behavior. These are categorized as:
Biological Factors:
Examples: Age, gender, body mass index, pubertal status, aerobic capacity, and agility.
Psychological Factors:
Examples: Self-esteem, motivation, competence, perceived health status, and health definitions.
Sociocultural Factors:
Examples: Race, ethnicity, education, socioeconomic status, and acculturation.
Prior Behavior
Refers to the frequency and patterns of similar past behaviors.
Influences future behavior through direct and indirect effects.
2. Behavior-Specific Cognitions and Affect
Perceived Benefits of Action
Anticipated positive outcomes that result from engaging in health-promoting behavior.
Perceived Barriers to Action
Real or imagined obstacles or costs associated with performing the behavior.
Perceived Self-Efficacy
Confidence in one’s ability to successfully organize and execute health-promoting behaviors.
Activity-Related Affect
Positive or negative feelings before, during, and after engaging in health-promoting behaviors.
A positive affect increases self-efficacy and the likelihood of action.
Interpersonal Influences
Cognitive factors arising from interactions with others, including:
Norms: Expectations from significant others.
Social Support: Emotional and practical encouragement.
Modeling: Learning behaviors by observing others.
Influences are typically from family, peers, and healthcare providers.
Situational Influences
Personal perceptions of the context or environment where health behavior occurs, which may facilitate or impede action.
Examples: Availability of options, environmental aesthetics, and contextual demands.
3. Behavioral Outcomes
Commitment to a Plan of Action
A planned strategy and clear intention lead to consistent health-promoting behaviors.
Immediate Competing Demands and Preferences
Competing Demands: Uncontrollable behaviors influenced by external factors, like work or family obligations.
Competing Preferences: Controllable alternative choices, such as selecting a healthy snack over an unhealthy one.
Health-Promoting Behavior
The ultimate goal of HPM, defined as behavior that leads to:
Optimal well-being.
Personal fulfillment.
Enhanced quality of life.
Assumptions of HPM
Each person has unique characteristics and experiences that influence actions.
Behavioral-specific knowledge and affect are critical motivational factors that can be modified through nursing interventions.
Health-promoting behaviors result in:
Improved health.
Enhanced functional ability.
Better quality of life across developmental stages.
Competing demands and preferences can derail intentions, requiring proactive strategies.
Applications of HPM in Nursing Practice
Community Health: Encouraging health-promoting behaviors in various populations.
Education: Enhancing awareness about benefits and strategies for maintaining health.
Clinical Settings: Tailoring nursing care to address barriers and improve self-efficacy.
Lifestyle Modification: Supporting individuals in developing habits like regular exercise, balanced diets, and stress management.